12 min read
When Is Hip Replacement Really Necessary?
Hip replacement may be considered when persistent pain, stiffness and loss of function continue despite appropriate non-surgical treatment.
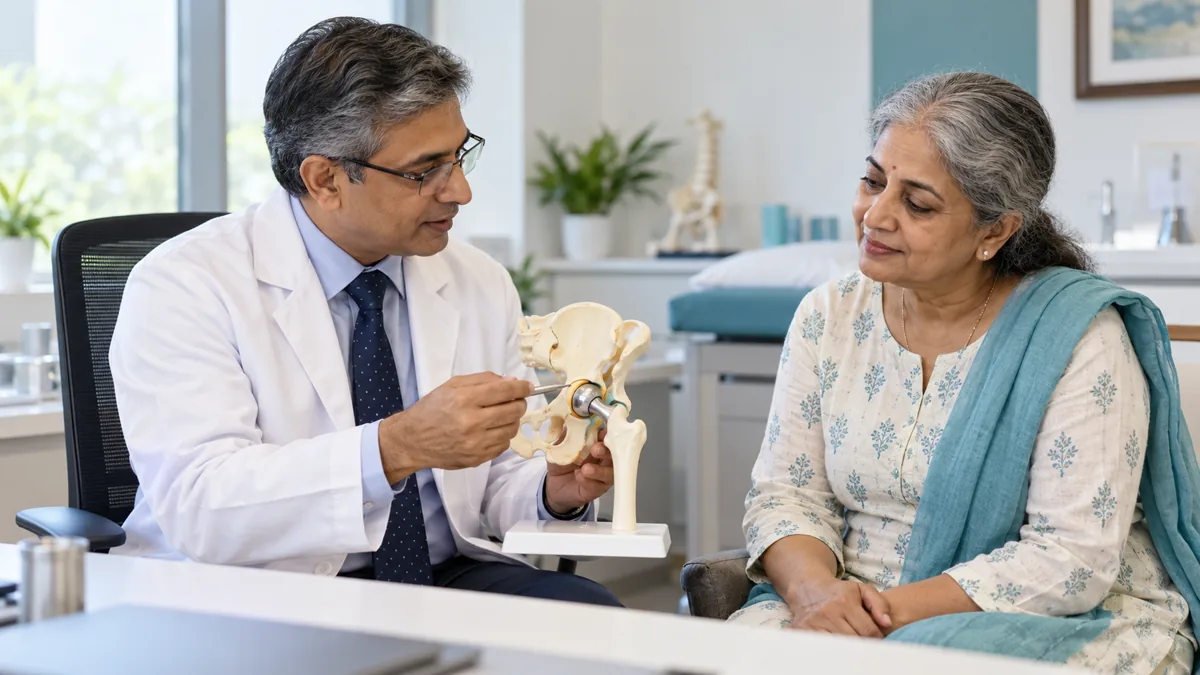
When Is Hip Replacement Really Necessary?
Hip pain can gradually shrink a person’s world. A short walk becomes difficult, getting into a car takes planning, sleep is interrupted, and ordinary tasks such as wearing shoes or climbing stairs begin to feel like major challenges. At that point, it is natural to ask whether hip replacement is really necessary or whether more time, physiotherapy or medication could still help.
There is no single pain score, age or X-ray finding that answers this question for everyone. Hip replacement is usually considered when symptoms have a substantial effect on daily life, the hip joint has damage that explains those symptoms, and appropriate non-surgical treatment is no longer providing enough relief. The final decision should be made through a careful discussion between the patient and an orthopaedic surgeon.
This guide explains the signs that may indicate it is time to consider surgery, what should usually be tried first, how the diagnosis is confirmed, and why waiting too long can sometimes be as unhelpful as rushing into an operation.
What Does Hip Replacement Surgery Actually Replace?
The hip is a ball-and-socket joint. The rounded head at the top of the thigh bone fits into a socket in the pelvis. Healthy cartilage allows these surfaces to move with very little friction. Osteoarthritis, inflammatory arthritis, avascular necrosis, an earlier injury or certain hip disorders can damage this smooth surface and make the joint painful and stiff.
In a total hip replacement, the damaged ball and socket surfaces are removed and replaced with artificial components made from combinations of metal, ceramic and medical-grade plastic. The purpose is not simply to create a better-looking X-ray. The main goals are to reduce pain, improve movement and help the patient return to meaningful daily activities.
For an overview of the procedure, implant choices and recovery planning, visit the hip replacement surgery page.
The Clearest Signs That Hip Replacement May Be Necessary
Hip replacement becomes a reasonable option when several findings point in the same direction. One symptom on its own is not enough. The pattern, severity, duration, examination findings and response to treatment all matter.
1. Pain is persistent and affects normal life
Arthritic hip pain is often felt deep in the groin, but it can spread to the front of the thigh, buttock or even the knee. Pain may begin with longer walks and later appear during shorter distances, standing, stairs or routine household activity. When pain repeatedly prevents necessary or valued activities despite treatment, surgery deserves consideration.
It is important to confirm that the pain is actually coming from the hip. Lower-back problems, nerve compression, outer-hip tendon disorders and other conditions can produce similar symptoms. Our guide to hip pain when walking explains how location and symptom patterns can help distinguish common causes.
2. Pain at rest or at night is disturbing sleep
Early hip arthritis may hurt mainly during weight-bearing activity. More advanced disease can cause pain while sitting, resting or lying in bed. Regularly waking because of hip pain, having to change position throughout the night, or needing frequent pain medicine to sleep suggests that the condition is having a substantial effect on health and quality of life.
3. Stiffness is limiting essential movement
A severely stiff hip can make it difficult to put on socks, tie shoelaces, sit comfortably, use the toilet, get into a vehicle or bend toward the floor. Some patients compensate by turning the leg outward, leaning to one side or asking others for help. Progressive loss of motion matters because it can affect independence even when the person describes pain as tolerable.
4. Walking distance and balance are declining
A limp, reliance on a walking stick and steadily decreasing walking distance can indicate meaningful loss of hip function. Avoiding movement because it hurts may also reduce leg strength, cardiovascular fitness and confidence. The surgeon will look at gait, muscle strength and whether another joint or the spine is contributing to the problem.
5. Appropriate non-surgical treatment is no longer enough
Hip replacement is generally not the first treatment for osteoarthritis. However, if a well-planned non-surgical programme has been tried for a sufficient period and the benefit is inadequate or short-lived, repeating the same measures indefinitely may not be useful. The UK National Institute for Health and Care Excellence recommends considering joint replacement referral when symptoms substantially affect quality of life and non-surgical management is ineffective or unsuitable. Its osteoarthritis guidance also recommends using clinical assessment rather than a numerical score alone.
6. Examination and imaging support the diagnosis
An X-ray may show loss of joint space, bone spurs, cysts or changes in the shape of the ball and socket. These findings can support the diagnosis, but they must match the patient’s symptoms and examination. Some people have marked X-ray changes with manageable symptoms, while others have severe limitations that seem less dramatic on an image. Surgery should treat a person, not an X-ray.
Conditions That Commonly Lead to Hip Replacement
Osteoarthritis is the most common reason for an elective total hip replacement. It develops as cartilage and other joint tissues change over time, leading to pain, stiffness and loss of function. Hip replacement may also be considered for:
- Inflammatory arthritis: Conditions such as rheumatoid arthritis can damage the joint despite medical treatment.
- Avascular necrosis: Reduced blood supply can cause the femoral head to collapse.
- Post-traumatic arthritis: A previous fracture or serious injury can lead to later joint degeneration.
- Childhood or developmental hip conditions: Abnormal hip shape can cause early wear and secondary arthritis.
- Some hip fractures: Depending on fracture type, age, bone quality and function, partial or total replacement may be recommended.
The underlying cause can affect the surgical plan, implant selection, likely complexity and expected recovery. This is why a complete history and appropriate imaging are essential.
What Should Usually Be Tried Before Surgery?
Non-surgical treatment should be tailored to the diagnosis, health status and goals. It is not a checklist that every patient must complete regardless of circumstances. For many people with hip osteoarthritis, a reasonable plan can include the following.
Therapeutic exercise and physiotherapy
Strengthening the muscles around the hip and improving mobility can reduce symptoms and support function, especially in mild to moderate disease. Exercise should be progressed according to tolerance. Forcing painful end-range movement or following an unsuitable generic routine can aggravate symptoms.
Activity modification
Switching from repeated high-impact activity to cycling, swimming or another lower-impact option may help a person stay active. A walking aid used in the correct hand can also reduce load and improve confidence. Activity modification should preserve movement, not lead to complete inactivity.
Weight management when appropriate
For a patient living with overweight or obesity, clinically appropriate weight management may reduce joint load and improve general surgical fitness. However, body mass index should not be used as the only reason to deny a referral. NICE specifically advises against excluding people from joint replacement referral solely because of age, sex, smoking, comorbidities or overweight and obesity.
Medication
Paracetamol, anti-inflammatory medicines or other pain strategies may be considered depending on medical history. These medicines are not safe for everyone. Kidney disease, stomach ulcers, cardiovascular risk, blood-thinning medication and other factors need review. Long-term self-medication without supervision can create avoidable harm.
Injection treatment
A corticosteroid injection may provide short-term relief for selected patients and can sometimes help clarify whether pain is arising from the hip joint. It does not reverse cartilage loss. Timing around planned surgery also needs discussion because an injection close to the operation may affect the treatment plan.
The American Academy of Orthopaedic Surgeons notes that physical therapy can improve pain and movement in mild to moderate hip osteoarthritis, and that a corticosteroid injection can provide short-term benefit. Its plain-language hip osteoarthritis summary also states that hyaluronic acid injections are not recommended for hip arthritis because they do not perform better than placebo.
When You Should Not Rush Into Hip Replacement
Surgery may not be the right next step when the diagnosis is uncertain, symptoms remain manageable, function is acceptable, or appropriate non-surgical care has not yet been tried. A patient should also pause if expectations are unrealistic. Hip replacement is intended primarily to relieve joint pain and improve everyday function. It does not restore a completely natural hip, guarantee unlimited movement or eliminate every possible source of pain around the pelvis and back.
Active infection, uncontrolled medical illness, untreated dental or skin infection, or other modifiable risks may require attention before elective surgery. Smoking cessation, glucose control, nutrition, anaemia management, medication review and strengthening may form part of pre-operative optimisation. This is preparation, not punishment, and should be personalised rather than used as a blanket barrier.
Can You Wait Too Long?
There is no universal deadline for elective hip replacement. If symptoms are mild and life remains satisfying, monitoring may be appropriate. However, waiting until mobility, strength and overall fitness have declined severely can make recovery more demanding. Persistent inactivity may also worsen deconditioning and independence.
On the other hand, once a patient has moderate-to-severe symptomatic osteoarthritis, has tried appropriate non-surgical treatment and has chosen surgery through shared decision-making, repeatedly delaying the procedure only to try additional ineffective treatments may not add value. The American College of Rheumatology and American Association of Hip and Knee Surgeons timing guideline addresses this specific situation.
The practical question is not, “Is the X-ray bad enough?” It is, “Is the damaged hip preventing me from living acceptably, have reasonable alternatives stopped helping, and do the likely benefits of surgery outweigh the risks for me?”
How an Orthopaedic Surgeon Decides Whether Surgery Is Appropriate
A thorough assessment usually includes:
- History: Where the pain is felt, what triggers it, whether it occurs at rest or at night, how long it has been present and which activities have been lost.
- Examination: Hip movement, strength, gait, leg length, tenderness, nerve function and assessment of the knee and lower back when relevant.
- Imaging: Weight-bearing or standard hip X-rays are often sufficient. MRI or other tests are reserved for situations where the diagnosis remains unclear or a different condition is suspected.
- Review of previous treatment: Exercise, physiotherapy, activity changes, medication, injections and the degree of benefit from each.
- Health and risk assessment: Heart and lung health, diabetes, infection risk, medications, bone quality, home support and rehabilitation needs.
- Shared decision-making: The patient’s goals, concerns and willingness to participate in recovery are weighed alongside the expected benefit and possible complications.
If you want an assessment focused on diagnosis and treatment options rather than an automatic surgical recommendation, you can learn more about Dr. Anshul Goel’s orthopaedic practice.
Benefits and Risks to Discuss Before Deciding
Hip replacement is a well-established operation and most appropriately selected patients experience substantial pain relief and improved movement. The NHS explains that it is commonly recommended when pain and stiffness have a major effect on life and other treatments have not worked. Its patient guide to why hip replacement is performed also identifies osteoarthritis as the most common reason.
All major surgery has risks. These include infection, blood clots, bleeding, dislocation, fracture, nerve or blood-vessel injury, leg-length difference, persistent pain, anaesthetic complications and the possibility that an implant may loosen or wear over time. Individual risk depends on health, diagnosis, anatomy, surgical complexity and other factors.
Recovery requires active participation. Many patients begin supported walking soon after surgery, then gradually build strength, balance and independence. The pace differs between individuals. Before giving consent, ask what pain relief and function are realistic for you, what restrictions may apply, how rehabilitation will work, and whom to contact if a problem develops.
A Practical Readiness Checklist
You may be ready for a formal hip replacement discussion if several of these statements are true:
- Hip pain regularly limits walking, stairs, sleep, work or self-care.
- Stiffness makes ordinary movements difficult.
- You have reduced or stopped activities that matter to you.
- The diagnosis has been confirmed through examination and appropriate imaging.
- A suitable non-surgical plan has not provided adequate relief.
- You understand that surgery has risks and recovery requires rehabilitation.
- Your goals are realistic and focused on pain relief and useful function.
- You are medically prepared, or willing to complete recommended optimisation first.
This checklist cannot determine candidacy. It can help you organise the conversation with a surgeon.
Frequently Asked Questions (FAQs)
1. At what age is hip replacement usually necessary?
There is no fixed age. Symptoms, joint damage, health, activity goals and expected benefit matter more than a birthday. Younger patients may face a greater lifetime chance of revision because they will use the implant for longer, while older adults require individual assessment of medical fitness and support.
2. Does bone-on-bone arthritis always mean I need surgery?
No. Severe joint-space loss on an X-ray supports the diagnosis, but surgery is usually based on the combination of symptoms, functional limitation, examination findings and response to treatment. A person with manageable symptoms may not need immediate replacement.
3. How bad should hip pain be before replacement?
There is no required pain number. Pain becomes more significant when it persistently interferes with sleep, mobility, independence, work or valued activity despite appropriate treatment. The overall impact matters more than a single score recorded on one day.
4. Can physiotherapy prevent hip replacement?
Physiotherapy can reduce symptoms and improve function, particularly in mild to moderate osteoarthritis. It cannot regrow severely damaged joint cartilage. Some people manage well without surgery for years, while others eventually choose replacement because pain and limitations progress.
5. Is groin pain a sign that I need hip replacement?
Deep groin pain is a common feature of hip-joint disease, but it does not by itself prove that replacement is needed. Tendon problems, hernia and other conditions can also cause groin pain. An examination and appropriate imaging are needed.
6. Should I wait until I can barely walk?
Not necessarily. Waiting until severe deconditioning, muscle weakness and loss of independence develop may make recovery harder. If pain and function are already substantially affected despite non-surgical care, an assessment can clarify whether continued waiting has a meaningful benefit.
7. How long does a hip replacement last?
Modern implants are designed for long-term use, but no implant comes with a guaranteed lifespan. Longevity varies with implant type, fixation, activity, anatomy, surgical factors and health. Your surgeon can discuss expectations that apply to your age and situation.
8. Can both hips be replaced?
Yes, when both joints are severely affected. The operations may be staged or, in selected patients, performed during the same admission. The safest approach depends on overall health, symptom severity, surgical risk, rehabilitation support and the surgeon’s assessment.
The Decision Is About Your Life, Not One Test
Hip replacement is really necessary when a clearly damaged hip is causing persistent, meaningful pain or disability, suitable alternatives are no longer effective or appropriate, and the expected improvement outweighs the individual risks. It should not be recommended because of age alone, and it should not be delayed simply because someone can still tolerate a shrinking quality of life.
If hip pain is limiting your movement, sleep or independence, book an orthopaedic appointment with Dr. Anshul Goel for a clinical assessment and an individual discussion of non-surgical and surgical options.
This article is for general educational purposes and does not replace a personal medical consultation, diagnosis or treatment plan. Seek urgent medical care after a fall or injury if you cannot bear weight, the leg appears shortened or deformed, or you develop sudden severe hip pain with fever or marked illness.
Related Articles
Sciatica vs Back Pain: Warning Signs That Need Urgent Spine Evaluation
Back pain with pain travelling into the leg may involve irritation of a nerve root.
Stress Fracture Symptoms in Runners: When Pain Is More Than a Shin Splint
Pain that becomes more focal and worsens with running may be more than a routine training ache.
Hip Pain When Walking: Causes That Need an Orthopedic Assessment
Hip pain while walking can come from the joint, surrounding muscles, spine, or an earlier injury.